
Aries PhysioCare
SPINE HEALTH

Degenerative Disc Disease (DDD):Pathomechanics, Pain Relief & Active Spine Conditioning

A complete guide to understanding Degenerative Disc Disease and how physiotherapy can help you move better, live pain-free, and stay active — at home.

Dr. Rhea Sharma

Dr. Rhea Sharma

Senior Physiotherapist

5 Feb 2026
12 min read
2.4k views
Degenerative Disc Disease Spine Rehabilitation

Disc Health

Moves You
Forward

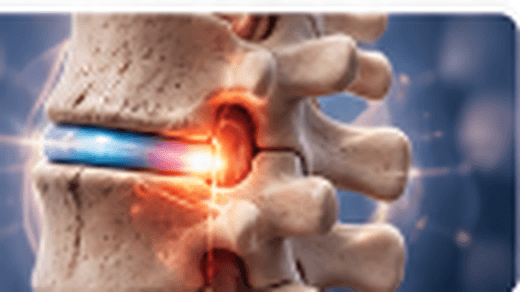
Lumbar Spine Disc Cross Section
1

Introduction: Understanding Lumbar Hyperlordosis

Lumbar lordosis is the natural inward C-shaped curve of the lower back that cushions axial shock during walking and running. However, when this inward curve becomes excessively exaggerated—a condition known as lumbar hyperlordosis or "swayback"—the delicate biomechanics of the pelvis and spine are disrupted. Characterized by an excessive anterior pelvic tilt where the tailbone points upward and the abdomen protrudes forward, hyperlordosis places immense compressive stress on the posterior facet joints and lumbar intervertebral discs.

2

Common Symptoms of Hyperlordosis

Postural distortion signs:

Exaggerated inward curve in the lower back with a prominent, protruding abdomen and buttocks
Aching tightness in the lower back after standing or walking for more than 15 minutes
Difficulty lying flat on your back on a firm mattress without a significant gap under the lumbar spine
Tightness in the front of the hips (psoas, rectus femoris) and lower back extensors
Pain aggravated by wearing high-heeled shoes or standing tall
Weakness or lack of engagement in the gluteal muscles during stair climbing
Occasional pinch in the facet joints when arching backward
3

Causes & Clinical Diagnosis

Primary biomechanical drivers:

Prolonged seated desk work causing chronic adaptive shortening of the iliopsoas muscles
Weakness and elongation of the deep abdominal wall (transversus abdominis, rectus abdominis)
Gluteal amnesia—inhibition of the gluteus maximus failing to pull the pelvis into neutral
Excess abdominal adiposity or pregnancy shifting the center of gravity forward
Diagnosis involves evaluating the Anterior Superior Iliac Spine (ASIS) to Posterior Superior Iliac Spine (PSIS) pelvic angle and the Thomas test for hip flexor contracture.
4

Pathophysiology & Biomechanical Impact

The anteriorly tilted pelvis forces the L4-L5 and L5-S1 facet joints into constant jammed approximation. The posterior annular disc fibers experience high shear forces, increasing the vulnerability to facet joint arthropathy, spondylolysis, and isthmic slippage.

5

Evidence-Based Physiotherapy Protocols

Deep myofascial release and active stretching of the iliopsoas, rectus femoris, and tensor fasciae latae (TFL)
Posterior pelvic tilt re-education in supine, quadruped, and standing positions
High-recruitment gluteal conditioning (deadlifts, hip thrusts, band bridges)
Core hollow-body and dead-bug progressions to reinforce neutral pelvic stability
6

Home Care & Ergonomic Strategies

  • Practice posterior pelvic tilts: while standing against a wall, flatten your lower back completely against it
  • Avoid wearing high-heeled shoes, which tip the pelvis forward and exaggerate lumbar lordosis
  • Sleep on your side with a pillow between knees, or on your back with a large pillow under your knees
  • Stand with equal weight distribution, actively engaging your lower abdominals and gluteals
7

When to Contact Us

Restore balanced pelvic alignment and relieve chronic lower back fatigue. Contact Aries PhysioCare for expert home physiotherapy and personalized pelvic alignment therapy.

Take Control of Your Spine Health Today!

Book a consultation with our expert physiotherapists and get a personalized care plan for lasting relief.
